
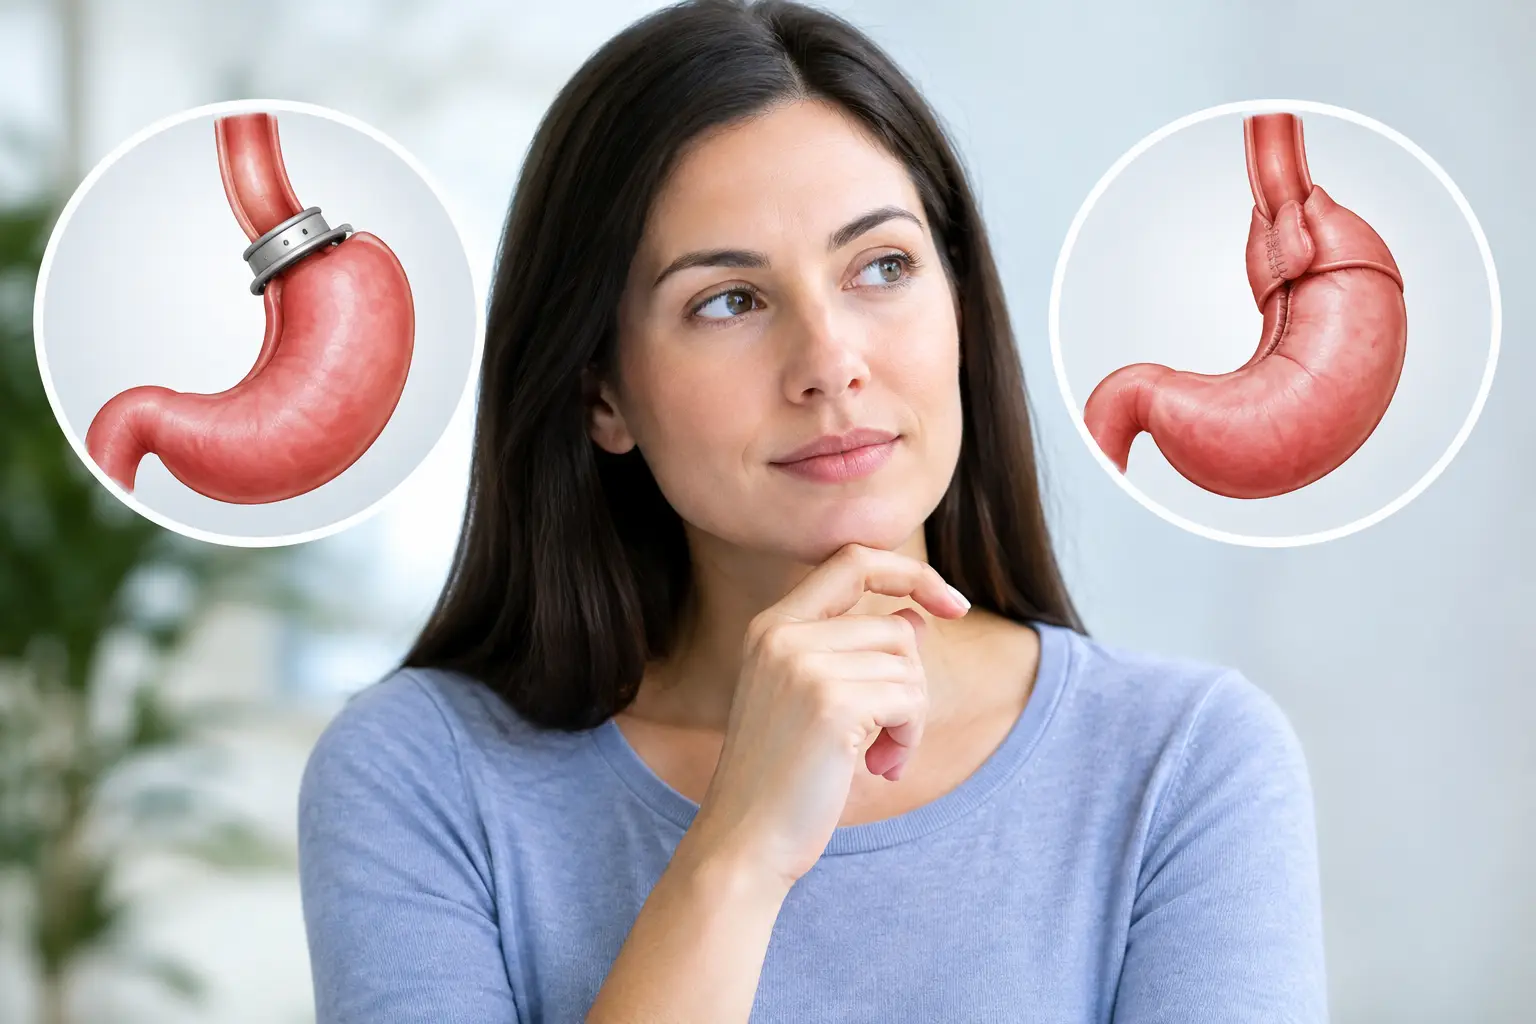
For people whose reflux continues despite medication, diet changes, and sleeping adjustments, the question is often not whether GERD needs more attention, but which procedure is the better fit. LINX versus fundoplication is a meaningful decision because both operations can control reflux effectively, yet they do so in different ways and may suit different anatomy, symptoms, and treatment goals.
The right choice begins with a careful evaluation, not a one-size-fits-all answer. A surgeon experienced in reflux and hiatal hernia repair can review the cause of your symptoms, the condition of your esophagus, and what matters most to you – from stopping daily medication to preserving the ability to belch or vomit comfortably.
What LINX and Fundoplication Treat
Both LINX and fundoplication are surgical treatments for gastroesophageal reflux disease, or GERD. GERD develops when the lower esophageal sphincter, the valve between the esophagus and stomach, does not close reliably. Acid and stomach contents can then move upward, causing heartburn, regurgitation, chest discomfort, chronic cough, hoarseness, or sleep disruption.
Many patients improve with acid-reducing medicines. But medication does not physically correct a weak valve or repair a hiatal hernia. When reflux is objectively confirmed and symptoms remain troublesome, surgery may offer a more durable approach.
A hiatal hernia is commonly addressed during either procedure. This occurs when part of the stomach moves upward through the diaphragm opening where the esophagus passes into the abdomen. Repairing the hernia helps restore the normal position of the stomach and supports reflux control.
LINX Versus Fundoplication: How the Procedures Differ
LINX magnetic sphincter augmentation
LINX is an FDA-approved device made of small magnetic beads connected in a flexible ring. During minimally invasive laparoscopic surgery, the ring is placed around the lower esophagus. The magnetic attraction helps keep the valve closed at rest, reducing reflux, while still allowing the ring to open when swallowing food or releasing gas.
For an appropriate candidate, LINX can reinforce the reflux barrier without creating a stomach wrap. Patients are generally encouraged to resume regular food textures soon after surgery, following their surgeon’s instructions, because swallowing helps the device and surrounding tissue adapt.
A potential advantage is that many patients retain a more natural ability to belch and vomit than they might after a traditional full fundoplication. However, LINX is not free of trade-offs. Temporary swallowing difficulty is common early in recovery, and some patients need further evaluation or treatment if dysphagia persists. The device can also be removed if necessary, although removal is another surgical procedure.
MRI considerations also matter. Current LINX devices have specific MRI compatibility conditions, while older devices may have more restrictive limits. Anyone considering LINX should discuss their device model and the likelihood of needing future MRI imaging with the surgical team.
Fundoplication
Fundoplication has been used for decades and remains a well-established surgical option for GERD. During this procedure, the upper part of the stomach, called the fundus, is wrapped around the lower esophagus to strengthen the reflux barrier. The wrap may be complete, often called a Nissen fundoplication, or partial, such as a Toupet fundoplication.
The type of wrap is not chosen casually. Esophageal movement, swallowing function, hernia size, prior surgery, and reflux severity can all influence whether a full or partial wrap is advisable. A partial fundoplication may be considered when esophageal motility is weaker, helping balance reflux control with the ability to swallow.
Fundoplication can be especially useful for patients with complex reflux anatomy or larger hiatal hernias. It does alter the shape of the upper stomach, which is different from the approach used with LINX. Some patients experience gas-bloat symptoms, difficulty belching, or trouble vomiting after a wrap, particularly early on. Careful technique and procedure selection can reduce these concerns, but they remain part of the conversation.
Which Procedure Controls Reflux Better?
Both procedures can provide substantial relief for appropriately selected patients. The more useful question is whether a procedure matches the cause of your reflux and the way your esophagus functions.
A patient with confirmed GERD, good esophageal motility, and a preference for magnetic sphincter augmentation may be an excellent LINX candidate. Another patient with a large paraesophageal hernia, significant esophageal motility concerns, or anatomy that requires a tailored reconstruction may be better served by fundoplication.
No operation can guarantee that every reflux symptom will disappear. Symptoms such as throat clearing, cough, chest pain, or hoarseness may have more than one cause. This is why confirming that reflux is truly responsible for your symptoms is so important before proceeding with surgery.
Testing That Guides an Individualized Recommendation
Before recommending LINX or fundoplication, a reflux surgeon may use several tests to understand what is happening at the lower esophagus and stomach. Upper endoscopy can identify inflammation, Barrett’s esophagus, a hiatal hernia, or other conditions that need attention. Ambulatory pH monitoring measures abnormal acid exposure, while impedance testing may detect non-acid reflux.
Esophageal manometry is particularly valuable when comparing LINX versus fundoplication. It measures how well the esophagus pushes food downward. Strong, coordinated swallowing function may support one treatment option, while reduced motility may change the surgical plan or favor a partial wrap.
Some patients also need a barium swallow study or gastric emptying evaluation. Delayed stomach emptying, for example, can contribute to bloating, nausea, and reflux-like symptoms. Treating only the valve without recognizing an underlying motility problem may not provide the relief a patient expects.
Recovery and Daily Life After Surgery
LINX and fundoplication are commonly performed laparoscopically or robotically through small incisions. This approach generally means less postoperative pain and a faster return to usual activities than open surgery, although recovery is still individual.
After LINX, patients usually follow a structured eating plan that includes regular swallowing of solid foods as directed. After fundoplication, diet progression is often more gradual, beginning with liquids or soft foods before advancing to regular textures. Temporary bloating, soreness, and changes in swallowing are possible with either procedure.
The timeline for returning to work depends on the physical demands of the job, the size and complexity of a hernia repair, and personal recovery. Many patients resume light activities within days and continue to improve over several weeks. Heavy lifting restrictions are especially important after hiatal hernia repair because excess strain can affect healing.
When Neither Option Is the Best First Choice
Not every patient with heartburn needs an anti-reflux operation. If testing does not show pathologic reflux, surgery may not address the true source of symptoms. Functional heartburn, medication side effects, esophageal sensitivity, and certain swallowing disorders require a different care plan.
Weight and previous bariatric surgery can also change the decision. For patients with obesity and severe GERD, gastric bypass may sometimes provide more effective reflux control while also supporting meaningful weight loss. For patients who developed reflux after sleeve gastrectomy, a revision strategy may be more appropriate than LINX or fundoplication. Prior abdominal operations, scar tissue, and existing implants all deserve careful review.
Insurance coverage and out-of-pocket costs may differ between procedures and plans. A knowledgeable office team can help patients understand authorization requirements, but the clinical recommendation should remain centered on safety, anatomy, and long-term benefit.
Choosing a Reflux Surgeon in Southwest Florida
GERD surgery is most successful when the procedure follows a thorough diagnostic workup and a candid discussion of trade-offs. At GI Surgical Specialists, the goal is to use the least invasive approach that can safely address the source of reflux, whether that involves LINX implantation, a tailored fundoplication, hiatal hernia repair, or another treatment pathway.
If reflux is limiting meals, sleep, work, or confidence in daily life, a surgical consultation can replace uncertainty with a plan built around your testing, your anatomy, and your priorities. The most helpful next step is not choosing a device or procedure from a list – it is having your symptoms heard and your options explained clearly.


